Disease Detectives
2027 season
On this page(19 sections)
Disease Detectives is epidemiology as a competition: the study of how disease, injury and health are distributed across groups of people, what drives that distribution, and how to use the answers to protect the public. You will not be asked which bacterium causes a disease or how long its incubation period is; when a question needs those facts, the test can supply them as background. What the event rewards is the way a field epidemiologist thinks. You read a scenario, decide whether something unusual is happening, organize the data into a table, compute the right measure, judge whether an exposure really caused the illness, and recommend what to do next.
Event format
| Item | 2027 rules (both divisions) |
|---|---|
| Team | Up to 2 students |
| Time | About 50 minutes |
| Notes | One 8.5" × 11" sheet, both sides, any content from any source; it may be laminated or kept in a sheet protector. No extra sheets, no affixed labels |
| Calculators | Up to two Class II calculators per team (scientific, non-programmable, non-graphing; see the calculator classes in the general rules) |
| Other | Writing utensils. No lab work, no eye protection, nothing to build |
| Test style | Written test, mostly built around case scenarios; the three topic areas carry about equal weight; questions aim at broad, basic understanding rather than detailed, advanced knowledge |
| Scoring | Highest score wins; preselected questions break ties; points reward correct answers, the quality of your reasoning and proper scientific method |
The event runs in partnership with the CDC, and the rules point to the glossary of CDC's Principles of Epidemiology in Public Health Practice as the vocabulary standard. That free online textbook is the closest thing the event has to a syllabus.
What the rules cover
The 2027 rules split the event into three areas of roughly equal weight: Background & Surveillance, Outbreak Investigation, and Patterns, Control, and Prevention. Questions are meant to be process-oriented: interpreting data and evaluating evidence, not reciting lists. The table paraphrases the outline (Division B rules pages B18–B19, Division C pages C22–C23).
| Area | Both divisions, all levels | Division B | Division C |
|---|---|---|---|
| Background & Surveillance | Clinical vs public health approach; history of epidemiology; roles of epidemiology and the steps in solving health problems; natural history and spectrum of disease; infectious (bacterial, viral, fungal, protist, prion) and noninfectious causes in broad terms; CDC glossary terms; surveillance: purpose, 5-step process, types, attributes | Same as both | Same as both |
| Outbreak Investigation | Case scenarios; experimental vs observational studies and the main designs (case-control, cohort, ecological, cross-sectional) with pros and cons; outbreak investigation steps; person–place–time and case definitions; reading outbreak data (epi curves, line listings, cluster maps, subdivided tables) and lab typing (PFGE gels, SNP mapping, the PulseNet network); agent–host–environment triad and chain of transmission; attack rate, relative risk, odds ratio, and judging whether the data support or require revising a hypothesis; Bradford Hill criteria vs Koch's and Evans's postulates, DAGs, sufficient–component cause models, GRADE | State & Nationals: study design, bias, error and confounding; herd immunity (concept) and vaccine effectiveness and efficacy | All levels: bias, error and confounding; choosing control groups and data collection methods; limitations; interpreting confidence intervals; stratification and adjusted rates; vaccine effectiveness and efficacy; herd immunity threshold, R₀ and effective R. Nationals: proposing control and prevention measures |
| Patterns, Control, and Prevention | Patterns and trends in charts, tables and graphs; risk, ratios, proportions, incidence proportion (attack rate), incidence rate, prevalence, death and mortality rates; strategies of disease control; prevention, including its scope and levels | Same as both | All levels: proposing prevention strategies once your analysis finds the cause. Nationals: strengths and weaknesses of proposed strategies; judging effectiveness from pre- and post-intervention data |
The two Division B State & Nationals items (bias/confounding, and herd immunity with vaccine effectiveness) are new to Division B in the 2027 rules. Division C's outline is unchanged.
Background: the public health way of thinking
Clinical approach vs public health approach
A physician practicing the clinical approach has one patient: take a history, examine, diagnose, treat, follow up. The public health approach treats the whole population as the patient. It runs as a loop: define the problem with data (surveillance), find the causes and risk factors (epidemiologic studies), develop and test interventions, then put them into wide use and evaluate them. A question asking what "the health department should do" wants population-level actions such as case finding, control measures and public communication, not a treatment plan for one person.
The two approaches depend on each other. Clinicians recognize and report unusual cases, which feeds surveillance; epidemiologists return findings, such as risk factors and screening recommendations, that change clinical care.
What epidemiology does
Epidemiology has two halves. Descriptive epidemiology organizes cases by person (age, sex, occupation, behavior), place (residence, workplace, travel) and time (onset date, season, trend). It answers who, where and when and generates hypotheses. Analytic epidemiology compares groups (exposed vs unexposed, or cases vs controls) to test those hypotheses and answers how and why.
CDC describes the core functions of epidemiology in public health as surveillance, field investigation, analytic studies, evaluation of programs, linkages with other agencies and data sources, and policy development. Its uses include assessing community health, informing individual decisions, completing the clinical picture of a disease, and searching for causes.
A short history
| Who | When | Contribution |
|---|---|---|
| Hippocrates | ~400 BCE | Explained disease through environment and behavior rather than the supernatural (Airs, Waters, Places); used the words endemic and epidemic |
| John Graunt | 1662 | Counted births and deaths in London's Bills of Mortality: the first systematic vital statistics |
| James Lind | 1747 | Compared treatments for scurvy among sailors; citrus fruit worked (an early controlled trial) |
| Edward Jenner | 1796 | Used cowpox material to protect against smallpox: the first vaccine |
| Ignaz Semmelweis | 1847 | Handwashing with chlorinated lime cut deaths from childbed fever |
| William Farr | from 1839 | Built England's system of vital statistics and disease classification; often called the father of modern surveillance |
| John Snow | 1854 | Mapped cholera deaths around the Broad Street pump and compared customers of two water companies; often called the father of field epidemiology |
| Florence Nightingale | 1850s | Used statistical diagrams to show that soldiers died mainly of preventable disease |
| Robert Koch | 1880s | Identified the bacteria of anthrax, tuberculosis and cholera; Koch's postulates |
| Framingham Heart Study | 1948– | Long-running cohort that identified cardiovascular risk factors |
| Doll and Hill | 1950s | Case-control and cohort studies linking smoking to lung cancer |
| Smallpox eradication | declared 1980 | Surveillance plus ring vaccination eliminated a human disease worldwide |

Natural history and spectrum of disease
The natural history of disease is the course an illness takes in one person when nothing interrupts it:
- Susceptibility: the person has not yet been exposed (or not yet affected) but is at risk.
- Subclinical disease: after exposure, pathologic changes begin without symptoms. For infections this gap is the incubation period; for chronic diseases the equivalent is the latency period.
- Clinical disease: symptoms appear; this is usually when diagnosis happens.
- Outcome: recovery, disability or death.
The spectrum of disease is the range of severity across people with the same infection or condition, from inapparent infection to death. Many infections, such as polio, hepatitis A and influenza, are often mild or silent, so reported cases are only the tip of an iceberg. People without symptoms can still be carriers: incubatory carriers (infectious before symptoms), convalescent carriers (still shedding after recovery) and chronic carriers (shedding for months or years).
Three properties of an infectious agent are tested often, and each has its own denominator:
The rules ask you to understand infectious causes (bacteria, viruses, fungi, protists, prions) and noninfectious causes (injuries, environmental and occupational exposures, toxic substances) only in broad terms. Know the categories well enough to reason: a prion is a misfolded protein with no nucleic acid, so it is not killed by ordinary sterilization; antibiotics treat bacteria, not viruses; a chemical exposure produces no person-to-person spread.
The epidemiologic triad and the chain of infection
The epidemiologic triad says that disease results from the interaction of an agent (a microbe, toxin or physical force), a susceptible host (age, immunity, genetics, nutrition, behavior) and an environment that brings them together (climate, crowding, sanitation, presence of vectors). Every control measure attacks at least one corner: treat or remove the agent, protect the host, or change the environment.
The chain of infection expands the triad into six links, and breaking any link stops transmission:
- Infectious agent.
- Reservoir: where the agent normally lives and multiplies: humans, animals (diseases passed from animals to humans are zoonoses) or the environment (soil, water).
- Portal of exit: respiratory secretions, feces, blood, skin lesions.
- Mode of transmission: direct (skin contact, sexual contact, droplet spray over a short distance) or indirect: airborne (tiny droplet nuclei that stay suspended), vehicle-borne (food, water, blood products, or contaminated objects called fomites) and vector-borne (insects or ticks; mechanical when the agent just rides on the vector, biological when it multiplies or develops inside it).
- Portal of entry: often matches the exit (respiratory to respiratory, fecal–oral).
- Susceptible host.

Vocabulary from the CDC glossary
| Term | Meaning |
|---|---|
| Endemic | The usual, constant presence of a disease in an area |
| Hyperendemic | Persistently high levels of a disease |
| Sporadic | Occurs irregularly and infrequently |
| Epidemic | More cases than expected for that population, place and time |
| Outbreak | Same as epidemic, usually for a more limited area |
| Cluster | Cases grouped in place and time that seem to be more than expected; the cause may be unknown |
| Pandemic | An epidemic across several countries or continents, affecting many people |
| Index case | The first case to come to the attention of investigators (not always the first case, the primary case) |
| Isolation | Separating sick people to stop spread |
| Quarantine | Restricting exposed but well people for the length of the incubation period |
| Risk | The probability that an event (illness, injury, death) will occur in a given time |
| Vector | A living carrier, usually an arthropod, that transmits an agent |
Surveillance
Public health surveillance is the ongoing, systematic collection, analysis and interpretation of health data, closely linked to getting those results to the people who can act on them. It establishes what is normal so departures stand out, and it tracks trends, measures disease burden, evaluates programs and sets priorities.
The 5-step surveillance process
The surveillance cycle is taught as five steps:
- Data collection: case reports from clinicians and laboratories, death certificates, hospital records, registries, surveys.
- Data analysis: organize by person, place and time; compute rates; compare with the baseline.
- Data interpretation: is the change real, or an artifact of a new test, a new case definition or better reporting?
- Data dissemination: send results to those who need them, for example in CDC's Morbidity and Mortality Weekly Report or WHO's Weekly Epidemiological Record.
- Link to action: use the findings to start control measures, change policy or allocate resources, then keep watching to evaluate the result.
A typical question describes an activity and asks which step it is. Publishing incidence data is dissemination; a health department closing a contaminated pool because of the numbers is the link to action.
Types of surveillance
| Type | How it works | Strength | Weakness |
|---|---|---|---|
| Passive | Providers and labs report notifiable conditions on their own initiative | Cheap; covers the whole jurisdiction | Underreporting; slow |
| Active | Health department staff contact providers or search records for cases | More complete and accurate | Costly; used in outbreaks or for priority diseases |
| Sentinel | Selected providers or sites chosen to represent an area or group report | High-quality trend data | Not population-wide; may be unrepresentative |
| Syndromic | Tracks symptom patterns before diagnosis: emergency-department complaints, pharmacy sales, school absences | Early warning | Nonspecific; false alarms |
Attributes of a good surveillance system
CDC's guidelines for evaluating surveillance systems list nine attributes. Simplicity (easy to run), flexibility (adapts to new needs), data quality (complete, valid data), acceptability (people and organizations are willing to take part), sensitivity (the proportion of true cases the system detects, or its ability to detect outbreaks), predictive value positive (the proportion of reported cases that really have the condition), representativeness (describes the whole population accurately over time), timeliness (speed between steps) and stability (reliable and available when needed).
Measuring disease frequency
Every calculation in this event is one of three kinds of fraction:
- Ratio: one quantity divided by another; numerator and denominator may be unrelated (male cases : female cases = 3 : 2).
- Proportion: a ratio in which the numerator is part of the denominator, usually written as a percent (40% of cases were children).
- Rate: a measure of how fast events happen, with time built into the denominator (cases per 1,000 person-years). In practice many "rates" in epidemiology, such as the attack rate, are really proportions over a stated period.
Crude, specific and adjusted rates
A crude rate describes a whole population. A specific rate describes one subgroup (age-specific, sex-specific, cause-specific). Comparing crude rates between populations with different age structures can mislead, because older populations die at higher rates regardless of anything else. An age-adjusted rate removes that difference. In direct standardization, you apply each population's age-specific rates to the same standard population and compare the resulting summary rates. Division C covers adjusted rates at every level.
Patterns and trends in data
Tests show you graphs and ask you to describe them. Time patterns include a secular trend (long-term change over years or decades, such as rising obesity), seasonality (influenza in winter, tick-borne disease in summer), cyclic patterns over several years, and the short-term spike of an outbreak. Choose the right display: a histogram (touching bars) for a continuous variable such as onset time, which is what an epi curve is; a bar chart for categories; a line graph for trends over time; a semilogarithmic graph to compare rates of change; a spot map for individual cases; and an area (choropleth) map for rates by region, which adjusts for population size. When summarizing a distribution, remember that the mean is pulled by outliers while the median is not; incubation periods are usually skewed, so the median is often reported.
Outbreak investigation
The steps
CDC's Principles of Epidemiology lists 13 steps. The order is logical, but in real investigations several happen at once, and control measures start as soon as anything is known.
- Prepare for field work: assemble the team, supplies and contacts; get approvals.
- Establish the existence of an outbreak: compare current cases with the expected baseline; rule out artifacts such as a new test or better reporting.
- Verify the diagnosis: review clinical findings and lab results.
- Construct a working case definition.
- Find cases systematically and record information in a line listing.
- Perform descriptive epidemiology: person, place, time; draw the epi curve.
- Develop hypotheses about source, mode of transmission and exposures.
- Evaluate hypotheses epidemiologically with an analytic study.
- As necessary, reconsider, refine and re-evaluate hypotheses.
- Compare and reconcile with laboratory and environmental studies.
- Implement control and prevention measures.
- Initiate or maintain surveillance.
- Communicate findings.
Descriptive epidemiology drives hypothesis generation: a sharp single peak points to one shared exposure; cases clustered in one dormitory point to that building.
Case definitions
A case definition is a standard set of criteria for deciding who counts as a case. It combines clinical criteria (symptoms, lab results) with limits of person, place and time: "diarrhea (three or more loose stools in 24 hours) beginning between 4 and 9 May in a student or staff member of Lincoln Middle School." Definitions are often tiered into confirmed (laboratory-confirmed), probable (typical clinical picture, no lab confirmation) and possible or suspect (some features). Early in an investigation a loose definition catches more cases (sensitive); later, a strict definition improves accuracy (specific).
Line listings
A line listing is a table with one row per case and columns for an identifier, demographics, clinical details, date and time of onset, lab results and key exposures. Keep it lean: the columns should be the ones you need to see patterns and build tables, not every detail of each person's life. It is the source for epi curves and 2 × 2 tables.
Epidemic curves
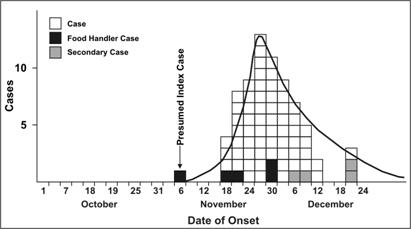
An epi curve is a histogram of cases by date or time of onset. Its shape suggests how the outbreak spread, its time course and where it is heading.
| Pattern | Shape | Typical example |
|---|---|---|
| Point source (common source, one exposure) | Steep rise, gradual fall; nearly all cases within one incubation period range | Food poisoning after one banquet |
| Continuous common source | Rise, then a plateau that lasts as long as the exposure does | A contaminated well used for weeks |
| Intermittent common source | Irregular peaks with no consistent spacing | A restaurant that sometimes serves a contaminated item |
| Propagated (person to person) | Successive, usually growing peaks about one incubation period apart | Measles in an undervaccinated community |
| Mixed | A point-source peak followed by propagated waves | Norovirus from a meal, then spread within households |

Reading cluster maps and subdivided tables
A cluster map (spot map) places each case where it lived, worked or was exposed; a tight group around one site suggests a common source, as at Broad Street. A subdivided table (stratified table) breaks the attack rate down by a second variable, such as age group, ward or shift, and is how you spot both where the risk concentrates and possible confounding.
Molecular epidemiology: PFGE, SNPs and PulseNet
When the same germ makes people sick in different cities, labs compare the bacteria's DNA to decide whether the cases share a source. Pulsed-field gel electrophoresis (PFGE) cuts the bacterial chromosome with an enzyme that cuts rarely, then separates the large fragments on a gel; the band pattern is a DNA fingerprint. Isolates with indistinguishable patterns probably came from the same source. Whole-genome sequencing compares isolates letter by letter and counts single-nucleotide polymorphisms (SNPs); isolates a few SNPs apart are very closely related. SNP analysis discriminates much more finely than PFGE: it can split isolates that look identical on a gel and can link isolates whose gel patterns differ slightly.
PulseNet is CDC's national network of public health and food regulatory laboratories. Each lab uploads its isolates' fingerprints to a shared database, so cases in different states caused by the same strain are linked into one outbreak even when no single health department sees more than a few cases. PulseNet began with PFGE in 1996 and has since moved to whole-genome sequencing.

Study designs
In an experimental study the investigator assigns the exposure (a vaccine, a drug, an education program). In an observational study the investigator only measures exposures people already have. Experiments give the strongest evidence of cause, but you cannot ethically assign a harmful exposure, so most outbreak and risk-factor work is observational.
| Design | How it works | Main measure | Best for | Weaknesses |
|---|---|---|---|---|
| Randomized controlled trial | Participants randomly assigned to intervention or control, often blinded | Risk ratio; vaccine efficacy | Strongest causal evidence; randomization balances known and unknown confounders | Expensive; impossible for harmful exposures; volunteers may not represent everyone |
| Community (field) trial | Intervention assigned to whole communities or healthy people (fluoridation, a vaccine campaign) | Rate comparison | Prevention programs | Costly; few units; contamination between groups |
| Cohort | Start with exposed and unexposed people free of disease; follow for outcomes. Prospective (forward in time) or retrospective (using past records) | Incidence, risk ratio | Common outcomes; several outcomes of one exposure; small defined outbreak groups (a wedding, a cruise) | Slow and costly if prospective; loss to follow-up; inefficient for rare diseases |
| Case-control | Start with people who have the disease and people who do not; compare past exposures | Odds ratio | Rare diseases; long latency; many exposures at once; outbreaks with no list of everyone exposed | Recall bias; choosing controls is hard; cannot compute incidence or risk |
| Cross-sectional | Measure exposure and disease at one point in time (a survey) | Prevalence, prevalence ratio | Burden of disease; planning; hypothesis generation | Cannot tell which came first |
| Ecological | Unit of analysis is a group (county, country), not a person | Correlation | Quick first look with existing data | Ecological fallacy: a group pattern may not hold for individuals |
Case reports and case series describe one or a few patients with no comparison group; they are how new diseases are first noticed but cannot test a hypothesis.
Measures of association
Analytic studies compare groups, and the comparison always starts with a 2 × 2 table. Put exposure in rows and outcome in columns, and label the cells the same way every time:
| Ill | Not ill | Total | |
|---|---|---|---|
| Exposed | a | b | a + b |
| Not exposed | c | d | c + d |
Confidence intervals (Division C)
A measure of association is an estimate; a 95% confidence interval shows the range of values compatible with the data. You only need to read them, never calculate them. Two rules handle nearly every question:
- If the CI for an RR or OR includes 1, the association is not statistically significant at the 5% level. OR = 1.8 (95% CI 0.7–4.6) could be no effect at all.
- A narrow CI means a precise estimate, usually from a large study. OR = 3.2 (95% CI 1.4–7.3) is significant but imprecise; RR = 3.2 (95% CI 2.9–3.5) is significant and precise.
A CI that sits entirely below 1, such as RR = 0.4 (0.2–0.7), indicates a significant protective association.
A full case scenario
Most points come from scenarios like this one, so practice the whole chain of reasoning.
The report. On Wednesday morning a school nurse reports that many students who went on Tuesday's field trip are vomiting. All 120 students and chaperones ate a packed lunch at noon on Tuesday; 35 are now ill, with onsets between 4 pm Tuesday and 2 am Wednesday.
Is it an outbreak? Thirty-five similar illnesses after one shared meal is far above any baseline. Verify the diagnosis with stool specimens and leftover food.
Case definition. "Vomiting or diarrhea beginning between noon Tuesday and noon Thursday in a student or adult who attended the field trip." Clinical criteria, person, place and time; no mention of any food.
Descriptive epidemiology. All onsets fall within a 10-hour span after one meal: a point-source epi curve. The scenario's background note gives a typical incubation of a few hours to about 15 hours, consistent with the lunch (onsets 4 to 14 hours after noon).
Analytic epidemiology. The whole exposed group is known, so run a retrospective cohort: interview all 120 people about what they ate.
| Food | Ate: ill / total | Attack rate | Did not eat: ill / total | Attack rate | RR |
|---|---|---|---|---|---|
| Turkey sandwich | 21 / 70 | 30.0% | 14 / 50 | 28.0% | 1.07 |
| Coleslaw | 30 / 45 | 66.7% | 5 / 75 | 6.7% | 10.0 |
| Apple juice | 30 / 100 | 30.0% | 5 / 20 | 25.0% | 1.2 |
The culprit has a high attack rate among those who ate it, a low attack rate among those who did not, and accounts for most cases: the coleslaw (30 of 35 cases ate it; RR 10.0). Apple juice was also consumed by 30 cases, but nearly everyone drank it, and the attack rates in drinkers and non-drinkers are almost the same.
The five cases who did not eat coleslaw. Expect a short-answer question on them. Reasonable explanations: they misremember what they ate (recall error, misclassification), a serving utensil cross-contaminated another item, they are secondary cases infected by a sick classmate, or they have an unrelated illness that happens to meet the case definition.
Laboratory and environment. Matching organisms in patients and leftover coleslaw, ideally with matching DNA fingerprints, confirm the source. An environmental investigation asks how the coleslaw was prepared and kept cold, and whether an ill food worker handled it.
Control, surveillance, communication. Discard the remaining product, exclude ill food workers until they recover, reinforce handwashing at the school, watch for secondary cases among families, and report to the school, the caterer and the state health department.
Causation
An association, even a strong one, is not proof of cause. The rules ask you to apply Bradford Hill's criteria to outbreak data and compare them with older and newer frameworks.
| Bradford Hill criterion | The question it asks |
|---|---|
| Strength | How large is the RR or OR? Strong associations are harder to explain by bias |
| Consistency | Have different studies, places and methods found the same association? |
| Specificity | Does the exposure lead to one particular outcome? (Weakest criterion: smoking causes many diseases) |
| Temporality | Did the exposure come before the disease? The only criterion that must be met |
| Biological gradient | Does more exposure produce more disease (dose–response)? |
| Plausibility | Is there a believable biological mechanism? |
| Coherence | Does the association fit what is already known about the disease? |
| Experiment | Does removing or reducing the exposure reduce the disease? |
| Analogy | Do similar exposures cause similar effects? |
Koch's postulates were designed for bacterial diseases: the organism is found in every case, can be isolated and grown in pure culture, causes the disease when given to a healthy susceptible host, and can be recovered again from that host. They break down for asymptomatic carriers, agents that cannot be cultured (many viruses, prions), diseases with several causes, and noninfectious diseases. Evans's postulates (1976) updated causal reasoning for modern epidemiology and immunology: disease should be more common in the exposed, exposure should precede disease, a measurable host response (such as antibodies) should follow exposure, and preventing or modifying the exposure should reduce disease.
Newer causal models in the 2027 outline:
- Sufficient–component cause model ("causal pies"): a disease happens when a complete sufficient cause forms, and each sufficient cause is a set of component causes. A necessary cause appears in every pie (Mycobacterium tuberculosis for tuberculosis, but exposure alone is not sufficient; host factors complete the pie). Blocking any one component prevents every case that pie would have produced, which is why one intervention can prevent a lot of disease.
- Directed acyclic graphs (DAGs): diagrams in which arrows show assumed causal effects and no path loops back on itself. They tell you which variables to adjust for. A confounder causes both exposure and outcome (adjust for it). A mediator lies on the path from exposure to outcome (do not adjust if you want the total effect). A collider is caused by both exposure and outcome (adjusting for it creates a false association).
- GRADE: a system for rating the certainty of a body of evidence as high, moderate, low or very low. Randomized trials start high and observational studies start low; certainty is downgraded for risk of bias, inconsistency, indirectness, imprecision or publication bias, and can be upgraded for a large effect or a dose–response gradient.
Bias, error and confounding
Any observed association has four possible explanations: chance (random error), bias (systematic error), confounding, or a true cause. Random error shrinks as studies get larger and shows up as wide confidence intervals. Systematic error does not shrink with sample size; it comes from how the study was designed or run.
| Problem | What goes wrong | Example | How to reduce it |
|---|---|---|---|
| Selection bias | Who enters or stays in the study depends on both exposure and outcome | Hospital controls who are sicker than the source population; volunteers; healthy worker effect; loss to follow-up in a cohort | Controls from the same source population as cases; high participation and follow-up |
| Recall bias | Cases remember past exposures differently from controls | Parents of a child with a birth defect search their memories harder | Use records; pick controls who also have an illness |
| Interviewer bias | Interviewers probe cases more thoroughly | Blinding; standardized questionnaires | |
| Misclassification | Exposure or disease recorded wrongly | Imperfect lab test; vague food history | Better measurement; non-differential misclassification biases toward RR = 1 |
| Confounding | A third variable linked to both exposure and outcome (and not on the causal path) distorts the association | Coffee looks like a cause of heart disease because coffee drinkers smoke more | Design: randomization, restriction, matching. Analysis: stratification, adjustment |
| Effect modification | The association truly differs between subgroups | A vaccine protects children better than older adults | Report each subgroup separately; do not average |
Choosing controls and collecting data
In a case-control study, good controls come from the same population that produced the cases and would have been counted as cases if they had become ill. Options include community controls (random-digit dialing, neighbors), friends nominated by cases, and hospital controls. Neighbors and friends may share the exposure (biasing the OR toward 1); hospital controls may have conditions linked to it. To reduce recall bias, choose controls who also have a serious illness, so both groups have searched their memories. Data can come from interviews, self-administered questionnaires, medical records, purchase records such as shopper cards, lab tests and environmental samples; records avoid recall problems but may be incomplete.
Stratification
To check for confounding, compute the measure separately within each level of the suspected confounder.
The rule: if the stratum-specific measures are similar to each other but different from the crude, the variable is a confounder; report an adjusted summary (for example, a Mantel–Haenszel estimate). If the stratum-specific measures are different from each other, the variable is an effect modifier; report the strata separately.
Screening tests
Screening finds disease in people without symptoms, and test-evaluation questions appear in surveillance, case definitions and secondary prevention. Set up the table with the test result in rows and true disease status in columns.
| Disease present | Disease absent | |
|---|---|---|
| Test positive | True positive (TP) | False positive (FP) |
| Test negative | False negative (FN) | True negative (TN) |
A highly sensitive test is what you want early, to rule disease out and to miss as few cases as possible during case finding. A highly specific test confirms disease and avoids labeling healthy people. Programs often screen with a sensitive test and confirm positives with a specific one. Screening programs have their own biases: lead-time bias (earlier diagnosis makes survival from diagnosis look longer even if death comes at the same time) and length-time bias (screening finds slow-growing disease, which has a better outlook anyway).
Vaccines, reproduction numbers and herd immunity
Immunity
Active immunity means your own immune system produces antibodies and memory cells, either naturally (after infection) or artificially (after vaccination). It takes days to weeks to develop but can last years. Passive immunity means receiving ready-made antibodies, either naturally (across the placenta or in breast milk) or artificially (immune globulin, antitoxin). It works immediately but fades within weeks to months.
Vaccine efficacy and effectiveness
Efficacy is how well a vaccine works under ideal, controlled conditions, measured in a randomized trial. Effectiveness is how well it works in real-world use, measured with observational designs (cohort, case-control, screening method).
Reproduction numbers and the herd immunity threshold
The basic reproduction number R₀ is the average number of secondary cases one infectious person causes in a population where everyone is susceptible. It depends on the contact rate, the chance of transmission per contact and how long a person stays infectious. The effective reproduction number ( or ) is the average at a given time, once some people are immune or control measures are in place. An outbreak grows while R is above 1 and shrinks when it falls below 1.
Herd immunity is the indirect protection that unvaccinated or non-immune people get when enough of the population is immune that transmission chains break. It protects those who cannot be vaccinated, such as newborns and people with weakened immune systems.

Disease control and prevention
Strategies of disease control
Control reduces the incidence, prevalence, illness or death from a disease to a locally acceptable level, and ongoing effort is needed to keep it there. Elimination reduces a disease to zero cases in a defined area (measles was declared eliminated from the United States in 2000). Eradication reduces it to zero worldwide permanently, so control measures can stop; only smallpox (in humans) and rinderpest (in cattle) have been eradicated.
Control measures are organized by the link of the chain they break:
| Target | Examples |
|---|---|
| Agent and reservoir | Treat cases; remove or treat infected animals; destroy contaminated food; disinfect surfaces |
| Transmission | Treat water; pasteurize; handwashing; safe food handling; vector control (draining standing water, insecticides); isolation; masks; condoms |
| Host | Vaccination; prophylactic medicines after exposure; quarantine of exposed people; nutrition; protective equipment |
Levels of prevention
| Level | Stage of natural history | Goal | Examples |
|---|---|---|---|
| Primordial | Before risk factors appear | Prevent the risk factors themselves | Policies that stop children from starting to smoke; walkable neighborhoods |
| Primary | Susceptibility | Prevent the disease from starting | Vaccination, seat belts, clean water, handwashing, condoms |
| Secondary | Subclinical, early disease | Detect and treat early to stop progression | Screening (mammograms, blood pressure checks), contact tracing with prophylaxis |
| Tertiary | Clinical disease | Limit disability and complications | Rehabilitation after stroke, diabetic foot care, physical therapy |
Scope of prevention
Prevention can target the whole population (fluoridating water, lowering salt in processed food) or a high-risk group (statins for people with high cholesterol). A population strategy can prevent more cases overall, because many cases arise from the large number of people at moderate risk, even though each individual benefits only a little; this is the "prevention paradox." CDC's Health Impact Pyramid ranks interventions by population impact. At the base are socioeconomic factors (poverty, education); next, changing the context to make individuals' default decisions healthy (fluoridated water, smoke-free laws, safety rules such as elevator weight limits); then long-lasting protective interventions (vaccines, a one-time screening); then clinical care; and at the top, counseling and education, which need the most individual effort per unit of impact.
Proposing and evaluating strategies (Division C)
A good proposal names the link of the chain or the level of prevention it targets, who carries it out, and how success will be measured. For example: "Require the caterer to keep coleslaw at or below 4 °C (40 °F) and train staff in handwashing (primary prevention, transmission link); measure success by surveillance for gastrointestinal illness after future events."
To evaluate an intervention, compare the outcome before and after, and ask whether the change could have happened anyway. Check for a secular trend (was the rate already falling?), regression to the mean (was the "before" period unusually bad?), and changes in how cases were counted. A comparison community without the program helps.
Strategy
- Divide the test by task. One partner takes the scenario and builds the tables and calculations while the other handles definitions, history and short answers; then swap to check each other's arithmetic.
- Build the note sheet around math and frameworks. Fit every formula from this guide with a one-line example, the 2 × 2 layout, epi-curve shapes, the outbreak steps, the 5-step surveillance cycle and attributes, the study-design table, Bradford Hill criteria, the bias table, levels of prevention and the Health Impact Pyramid. Leave out pathogen lists; the rules exclude them as required knowledge and let tests supply such facts when needed.
- Show work every time. Write the formula, substitute the numbers and state units ("per 100", "per 1,000 person-years"). Graders give partial credit and score reasoning.
- Answer in specific sentences. "The case definition must not include the salad, or every case is exposed by definition" earns more than a vague paragraph.
- Skim the whole test first. Late scenarios are often worth the most points.
Common pitfalls
How tournaments test this
The site's archive holds 21,790 Disease Detectives questions from public tournament tests across the 2016-17 to 2025-26 seasons (12,176 Division C, 8,227 Division B, 1,387 shared), plus about 39,000 more in the practice bank.
- Format. 58% of archived questions are free response and 34% multiple choice; the rest are numeric, true/false and select-all. Expect to write sentences, since scoring rewards reasoning.
- Topics (tags overlap): general epidemiology and vocabulary 24%, statistics and calculations 23%, outbreak investigation 20%, study design 18%, pathogens and transmission 18%, prevention 15%, surveillance 9%. Many "pathogen" questions on older tests are disease trivia the rules exclude; the transmission and agent-category questions still apply.
- Task shapes. About one question in seven is built on a case scenario (a camp, a cruise ship, a school, a wedding). Common tasks: compute attack rates, RR, OR and prevalence from a table; classify an epi curve; write a case definition; choose a study design and a control group; apply a Bradford Hill criterion; name the level of prevention or type of surveillance; calculate a herd immunity threshold.
- Recurring terms. "Case definition" appears in over 1,000 questions; "attack rate", "relative risk" and "odds ratio" in roughly 800–950 each; "herd immunity" in about 700; "Bradford Hill criteria" in about 400; "positive predictive value", "case fatality rate", "secondary attack rate" and "healthy worker effect" in over 100 each.
- Most common correct answers: cohort, case-control, primary/secondary/tertiary prevention, vector, fomite, epidemic, pandemic, endemic, cluster, virulence, pathogenicity, active, passive, sentinel and syndromic surveillance, public health approach, temporality, cross-sectional, John Snow, Edward Jenner, herd immunity, zoonosis, reservoir.
Test yourself
Real questions from public tournament tests. Each one links to the full test.
- 1
Who is credited with first shifting explanations of disease from supernatural causes to rational observation?
Practice more Disease Detectives questions →
- 1
Investigators identify children with asthma and compare their past exposures to those without asthma. This study is:
Practice more Disease Detectives questions →
- 1
If the VOC-related cancer has a very high mortality rate and patients die quickly after diagnosis, how will this affect the observed Prevalence?
From: Crystal Lake Central Invitational - IL, 2025-26, Division C
Practice more Disease Detectives questions →
References and further reading
- CDC, Principles of Epidemiology in Public Health Practice, 3rd ed., including the glossary the rules name: https://archive.cdc.gov/www_cdc_gov/csels/dsepd/ss1978/index.html
- CDC Field Epidemiology Manual, "Conducting a Field Investigation": https://www.cdc.gov/field-epi-manual/php/chapters/field-investigation.html
- CDC, Updated Guidelines for Evaluating Public Health Surveillance Systems (MMWR 2001): https://www.cdc.gov/mmwr/preview/mmwrhtml/rr5013a1.htm
- CDC PulseNet: https://www.cdc.gov/pulsenet/
- Hill AB, "The Environment and Disease: Association or Causation?", Proc R Soc Med 1965: https://doi.org/10.1177/003591576505800503
- Rothman KJ, "Causes", Am J Epidemiol 1976 (sufficient–component cause model): https://doi.org/10.1093/oxfordjournals.aje.a112335
- Evans AS, "Causation and disease: the Henle-Koch postulates revisited", Yale J Biol Med 1976.
- Guyatt GH et al., "GRADE: an emerging consensus on rating quality of evidence and strength of recommendations", BMJ 2008: https://doi.org/10.1136/bmj.39489.470347.AD
- Fine P, Eames K, Heymann DL, "Herd immunity: a rough guide", Clin Infect Dis 2011: https://doi.org/10.1093/cid/cir007
- Farrington CP, "Estimation of vaccine effectiveness using the screening method", Int J Epidemiol 1993: https://doi.org/10.1093/ije/22.4.742
- Frieden TR, "A Framework for Public Health Action: The Health Impact Pyramid", Am J Public Health 2010: https://doi.org/10.2105/AJPH.2009.185652
- Science Olympiad (official rules and the event's CDC resources): https://www.soinc.org
- SciOly Wiki, Disease Detectives: https://scioly.org/wiki/index.php/Disease_Detectives
- Practice more: the Scio.ly test archive has hundreds of public Disease Detectives tests.
Official references
Sample notesheet
Download a printable, rule-compliant sample notesheet. Customize with your notes.